Opening the book…
Search Fundamentals of Biochemistry
(Learning goals written by Claude, Sonnet 4.6, Anthropic)
Ketone Body Structure, Synthesis, and Metabolic Context
- Identify the three ketone bodies (acetoacetate, D-β-hydroxybutyrate, and acetone), explain the metabolic conditions — fasting, starvation, uncontrolled diabetes, and ketogenic diet — that lead to their overproduction, and describe why ketone bodies are essential fuel molecules that can cross the blood-brain barrier while albumin-bound fatty acids cannot.
- Explain the biochemical reason ketone bodies accumulate when carbohydrate metabolism is impaired: the diversion of oxaloacetate to gluconeogenesis reduces TCA cycle activity, preventing acetyl-CoA entry into the cycle and forcing it into ketogenesis.
- Trace the three key enzymatic steps of ketogenesis — thiolase-catalyzed Claisen condensation of two acetyl-CoA to acetoacetyl-CoA, HMG-CoA synthase-catalyzed condensation with a third acetyl-CoA via a ping-pong mechanism with a covalent acetyl-Cys intermediate, and HMG-CoA lyase-catalyzed C–C bond cleavage to release acetoacetate — explaining the mechanistic logic of each C–C bond formation or cleavage event.
- Explain why HMG-CoA synthase is a branch point enzyme whose product (HMG-CoA) is directed either toward ketone body synthesis (via HMG-CoA lyase) or toward cholesterol synthesis (via HMG-CoA reductase, the target of statins), and explain why statins affect cholesterol but not ketogenesis.
Ketolysis and Tissue-Specific Utilization
- Describe the pathway of ketolysis in extrahepatic tissues — conversion of D-β-hydroxybutyrate to acetoacetate, activation to acetoacetyl-CoA by succinyl-CoA:3-oxoacid-CoA transferase (SCOT), and thiolytic cleavage to two acetyl-CoAs — explaining why the liver cannot use its own ketone bodies due to the absence of SCOT expression.
- Explain how the monocarboxylate transporters MCT1 and MCT2 facilitate ketone body uptake into peripheral tissues, and describe the fate of acetone as a dead-end metabolite excreted in urine and breath.
Hormonal Regulation and Clinical Significance
- Describe how low insulin levels coordinately activate ketogenesis by increasing lipolysis (via disinhibition of hormone-sensitive lipase), reducing malonyl-CoA (via inactivation of acetyl-CoA carboxylase), disinhibiting CPT-1 to increase mitochondrial fatty acid uptake, and increasing HMG-CoA synthase activity.
- Explain the pathophysiology of diabetic ketoacidosis (DKA) — connecting impaired glucose utilization to gluconeogenesis, oxaloacetate depletion, acetyl-CoA accumulation, and ketone body overproduction — and describe the clinical consequences, including metabolic acidosis, hyperglycemia-driven dehydration, compensatory hyperventilation, and respiratory alkalosis.
Some of the material below derives from Kolb et al. BMC Medicine (2021) 19:313 https://doi.org/10.1186/s12916-021-02185-0. Creative Commons Attribution 4.0 International License, http://creativecommons.org/licenses/by/4.0/.
Introduction
Ketone bodies are the name given to two molecules, acetoacetate (a ketone) and D-β-hydroxybutyrate (its reduction product), that derive from the condensation of acetate in the form of acetyl-CoA. Their structures are shown in Figure \(\PageIndex{1}\).

They are synthesized when acetyl-CoA concentrations are high. That would occur under a couple of conditions:
- fatty acids are being mobilized in adipocytes and broken down into acetyl-CoA through β-oxidation in the mitochondria;
- the acetyl-CoA produced can not enter the Krebs cycle, leading to the buildup of acetyl-CoA in the matrix.
The latter condition arises when carbohydrate metabolism is compromised, slowing the citric acid cycle. This occurs when the citric acid cycle intermediate oxaloacetate is diverted from the cycle for gluconeogenesis. Pyruvate, another source of acetyl-CoA (through pyruvate dehydrogenase), is also depleted in gluconeogenesis. Of course, we are describing conditions in the liver, the major site of gluconeogenesis and ketone body synthesis.
These conditions also occur in the underfed or starving state, when glycogen stores are exhausted and fatty acid reserves are used for energy. Likewise, these conditions are met in diabetes, when glucose may be abundant in the circulation, but its entry into the cell is compromised by defects in insulin signaling.
Fatty acids released by adipocytes into the blood are bound to serum albumin for transport to tissues. However, albumin bound to fatty acids does not cross the blood-brain barrier. Ketone bodies are small and water-soluble, allowing them to cross the blood-brain barrier and deliver a soluble equivalent of fatty acids to the brain and other tissues during times of energy need. Ketone bodies can be considered solubilized and easily transportable equivalents of fatty acids. They have low pKa values of 3.6 (acetoacetate) and 4.7 (D-β-hydroxybutyrate), so they can lead to "ketoacidosis" in diabetics. Acetone is a non-acidic, sweet-smelling molecule that can be detected in the breath of diabetics. It is produced spontaneously and also catalytically through the decarboxylation of the beta-keto acid acetoacetate. It is also considered a ketone body.
The blood-brain barrier (BBB) protects the entire nervous system (CNS). Endothelial cells line the surface of all blood vessels. In the CNS, additional structures prevent many molecules from entering. Tight junctions form a watertight barrier that prevents molecules from moving between cells, while adherens junctions provide mechanical strength and tether cells together. The basement membrane, glial cells, and pericytes provide additional protection. Additionally, drug efflux transporters (ABC transporters) move xenobiotics (foreign toxic molecules) back across the barrier.
Nonpolar molecules like dioxygen and low-molecular-weight nonpolar molecules can cross the BBB by simple diffusion. Other polar molecules, such as glucose and amino acids, cross via transporters. Larger substances can enter via receptor-mediated endocytosis. Albumin, the major carrier of free fatty acids, like other proteins, does not readily pass through the barrier. Neither do albumin: ligand complexes.
Figure \(\PageIndex{2}\) represents the blood-brain barrier.

Figure \(\PageIndex{2}\): Structure of the blood-brain barrier. Wilhelm et al. Int. J. Mol. Sci. 2013, 14, 1383-1411; doi:10.3390/ijms14011383. Creative Commons Attribution License
(http://creativecommons.org/licenses/by/3.0/).
In this section, we will explore the synthesis and utilization of ketone bodies. The synthesis pathway is called ketogenesis, and the degradation pathway is called ketolysis. Ketone body production and utilization are closely tied to fatty acid metabolism, making it appropriate to discuss them immediately after fatty acid oxidation. An overview of both ketogenesis and ketolysis is shown in Figure \(\PageIndex{3}\).

Figure \(\PageIndex{3}\): Overview of the ketogenesis (left) and ketolysis (right) pathways. FFA, free fatty acids; mThiolase,
mitochondrial thiolase; HMGCS2, hydroxy methylglutaryl-CoA synthase; HMGCL, HMG-CoA lyase; BDH1, mitochondrial βOHB dehydrogenase; MCT1/2, monocarboxylate transporter 1 and 2; SCOT, succinyl-CoA:3-oxoacid-CoA transferase; CS, citrate synthase. Kolb et al. BMC Medicine (2021) 19:313
https://doi.org/10.1186/s12916-021-02185-0 Creative Commons Attribution 4.0 International License. http://creativecommons.org/licenses/by/4.0/.
Most acetoacetate is reduced to its β-hydroxybutyrate product for blood transport. It can be spontaneously or enzymatically converted to acetone, as it is a β-ketoacid with a built-in electron sink that stabilizes the negative charge in the transition state and intermediate. When ketone bodies enter cells, β-hydroxybutyrate is converted back to acetoacetate, which is then converted to acetyl-CoA.
Ketogenesis: The details
Figure \(\PageIndex{4}\) shows the chemical structures of all intermediates in synthesizing ketone bodies.

We'll study three ketogenesis reactions in more detail below.
Reaction 1: Thiolase
We presented the thiolase mechanism in Step 4 of mitochondrial β-oxidation of fatty acids using the enzyme acetyl-CoA acetyltransferase (ACAT1), also known as 3-ketoacyl-CoA thiolase. The final step in the beta-oxidation pathway involves cleavage of the bond between the alpha and beta carbon by CoASH. Beta-keto thiolase catalyzes this thiolytic reaction (as opposed to cleavage by water, a hydrolysis reaction). The reaction produces one molecule of acetyl-CoA and a fatty acyl-CoA that is two carbons shorter. The process repeats until the even-chain fatty acid is completely converted into acetyl-CoA. The enzyme is reversible and can also catalyze the Claisen condensation of two acetyl-CoA molecules to form acetoacetyl-CoA. This reaction occurs in the first step of ketogenesis. This step makes a C-C bond.
Reaction 2: HMG-CoA Synthase
This enzyme catalyzes the condensation of acetoacetyl–CoA (AcAc-CoA) and acetyl–CoA (Ac-CoA) to form 3-hydroxy-3-methylglutaryl (HMG)-CoA, forming a C-C bond. Forming C-C bonds is critical to all biosynthesis. It's not a simple process. As we saw with pyruvate dehydrogenase, cofactors such as thiamine pyrophosphate are often used. The reverse process, breaking a C-C bond, is also difficult unless the atoms are activated. One way to activate a carbon atom is to oxidize it through hydroxylation, often using dioxygen in reactions catalyzed by cytochrome P450. Likewise, C-C bond formation often occurs through the reaction of radicals in hemolytic reactions or through the rearrangement of key ionic intermediates. Radical reactions can occur between a carbon-free radical and heme derivatives. Radical reactions involve heme cofactors (as in P450), non-heme iron proteins (where the iron ion can cycle between different oxidation states), flavoproteins (in which the flavin can undergo both 1 and 2 electron redox steps), radical S-adenosylmethionine (SAM) enzymes, and cobalamins.
HMG-CoA synthase is somewhat unique in forming a C-C bond by activating the methyl group of acetyl-cysteine. The acetyl group comes from an acyl-CoA "donor". The enzyme catalyzes the first committed step in forming complex isoprenoids (such as cholesterol) and ketone bodies. The product, 3-hydroxy-3-methylglutaryl HMG–CoA, can either be reduced by HMG-CoA reductase to form mevalonate, which leads to cholesterol synthesis, or cleaved by the enzyme HMG-CoA lyase to produce acetoacetate, a ketone body.
Because it catalyzes the first step in cholesterol synthesis, HMG-CoA reductase has been a primary target of drug therapy to reduce high serum cholesterol levels, which are often associated with cardiovascular disease. Over 200 million people worldwide are on statins, the primary drugs used to block HMG-CoA reductase activity. Luckily, statins don't affect HMG-CoA lyase. Gram-positive bacteria also require the mevalonate pathway.
HMG-CoA synthase catalyzes a bisubstrate reaction that displays ping-pong kinetics, which is characteristic of a covalent enzyme intermediate. The first substrate binds to the enzyme and transfers an acetyl group to a nucleophilic Cys 111 in the active site, forming an acetyl-Cys 111 intermediate. Free CoA departs. Next, the second substrate, acetoacetyl-CoA, binds and condenses with the acetyl group donated by acetyl-Cys 111. This condensation involves an enolate. Figure \(\PageIndex{5}\) shows a plausible reaction mechanism.

Figure \(\PageIndex{5}\): Reaction mechanism for HMG-CoA synthase
Hence, the reaction consists of three parts: acetylation/deacetylation, condensation/cleavage involving an enolate intermediate, and C-C bond formation and hydrolysis/dehydration. Figure \(\PageIndex{6}\) shows an interactive iCn3D model of the Staphylococcus aureus HMG-COA Synthase with bound HMG-CoA and acetoacetyl-CoA (1XPK)

 Figure \(\PageIndex{6}\): Staphylococcus aureus HMG-COA Synthase with bound HMG-CoA and acetoacetyl-CoA (1XPK). (Copyright; author via source). Click the image for a popup or use this external link: https://structure.ncbi.nlm.nih.gov/i...deiFs7JceE5H76
The biologically active unit (homodimer) is shown, with each monomer shown in a different color. The A chain (light cyan) has bound HMG-CoA (HMG) while the B chain (light gold) has acetoacetyl-CoA (CAA) bound. The Glu 79, Cys 111, and His 233 in each subunit are shown in CPK sticks and labeled. Note that Cys 111 is covalently modified in each subunit.
Figure \(\PageIndex{7}\) shows an interactive iCn3D model of the human 3-hydroxy-3-methylglutaryl CoA synthase I with bound CoASH (2P8U)
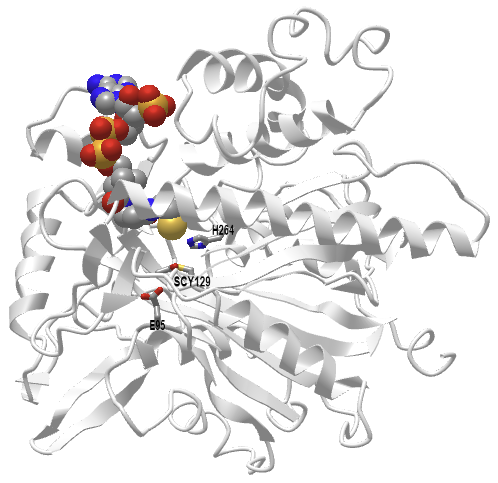
Figure \(\PageIndex{7}\): Human 3-hydroxy-3-methylglutaryl CoA synthase I (monomer) with bound CoASH (2P8U). (Copyright; author via source). Click the image for a popup or use this external link: https://structure.ncbi.nlm.nih.gov/i...xxEoUfecTk3eL6
The active site side chains are numbered differently (Glu 95, Cys 129, and His 264) than the S. aureus protein. This model shows only the monomer.
Reaction 3: HMG-CoA Lyase
The lyase reaction cleaves a C-C bond to produce acetyl-CoA and acetoacetate. A gene knockout of this gene in mice is lethal. Figure \(\PageIndex{8}\) shows a plausible mechanism for the reaction.

Figure \(\PageIndex{9}\) shows an interactive iCn3D model of the human HMG-CoA lyase with the competitive inhibitor hydroxyglutaryl-CoA (HG-CoA)(3MP3)

Figure \(\PageIndex{9}\): Human HMG-CoA lyase with inhibitor HG-CoA (3MP3). (Copyright; author via source). Click the image for a popup or use this external link: https://structure.ncbi.nlm.nih.gov/i...VJBWxXpcKQyij8
Only one subunit of the homodimer is shown. The key residues involved in catalysis and binding (Arg41, Asp42, His233, His235, and Cys266) are shown in sticks, with CPK colors and labels. The competitive inhibitor, 3-hydroxyglutaryl-CoA (without the methyl group), is shown in CPK-colored sticks. The S-stereoisomer of HMG-CoA or the inhibitor binds, not the R-isomer. Water may shuttle protons between Asp 42 and the C3 hydroxyl of HMG-CoA. Arg 41 facilitates the proper enol/keto tautomerization during enolization of the product. Mutation of Arg 41 drastically reduces catalysis.
We won't discuss the remaining enzymes in detail since we have encountered variants of NAD+/NADH dehydrogenase reactions before. The acetoacetate decarboxylase hastens the already spontaneous decarboxylation of the β-keto ester acetoacetate.
Regulation of Ketogenesis
Hormones such as glucagon, cortisol, thyroid hormones, and catecholamines can upregulate ketogenesis, thereby mobilizing fatty acids. Insulin is the primary hormonal regulator of this process.
Insulin regulates many key enzymes in the ketogenic pathway, and a low insulin state triggers the process. A low insulin state leads to:
- Increased free fatty acids (FFAs) arising from decreased inhibition of hormone-sensitive lipase
- Increased uptake of FFAs into the mitochondria arising from decreased activation of acetyl-CoA carboxylase, decreasing malonyl-CoA, which disinhibits Carnitine Palmitoyltransferase 1 (CPT1)
- Increased production of ketone bodies arising from increased HMG-CoA activity
Ketolysis: Utilization of ketone bodies
Figure \(\PageIndex{10}\) shows the chemical steps in using ketone bodies.

Since we have encountered similar reactions, we will not discuss their detailed mechanisms.
Most organs and tissues can utilize ketone bodies as an energy source. They are a major energy source for the brain when glucose is unavailable. That makes sense because fatty acids can't cross the blood-brain barrier. The heart prefers fatty acids for energy but can also use ketone bodies. The liver produces them but does not utilize them, as the gene for step 2, β-ketoacyl-CoA transferase, is not transcribed. D-β-hydroxybutyrate is first converted to the other ketone body, acetoacetate, for the pathway to continue. The net result is the formation of two acetyl-CoAs that can then enter the citric acid cycle for ATP production. Acetone is a dead-end ketone body and is excreted in the urine or eliminated in the breath.
Clinical Significance
An overproduction of ketone bodies through increased ketogenesis can cause ketoacidosis (given the pKas of the ketone bodies). One type is diabetic ketoacidosis (DKA) in Type I and II diabetes, which impairs glucose use. This leads to liver gluconeogenesis and depletes oxaloacetate and pyruvate, impairing acetyl-CoA entry into the citric acid cycle.
Upon presentation, patients are often severely dehydrated due to hyperglycemia. High blood glucose increases vascular osmotic pressure and reduces kidney water reabsorption. They often have accompanying symptoms like confusion, nausea, vomiting, and abdominal pain. Because of acidosis, patients often breathe deeply and rapidly to eliminate carbon dioxide, which can lead to respiratory alkalosis. Ketoacidosis can also occur with severe alcoholism and prolonged starvation.
The ketogenic diet, characterized by high-fat, low-carbohydrate intake, can lead to weight loss. It shifts metabolism to more closely resemble fasting. Its long-term effects are not clear, but some have suggested the use of ketone-based drugs to mimic the effect of ketone bodies. Fasting can also lead to a ketogenic state, and it has been used for the treatment of epilepsy before the drug became available. It is important to differentiate this attempt to induce a ketogenic state from diabetic ketoacidosis.
Summary
(Summary written by Claude, Sonnet 4.6, Anthropic)
This chapter describes ketone body metabolism — the synthesis (ketogenesis) and utilization (ketolysis) of acetoacetate, D-β-hydroxybutyrate, and acetone — as an integral part of fatty acid catabolism that provides alternative fuel for peripheral tissues during glucose deprivation.
Ketone bodies arise when acetyl-CoA accumulates in the mitochondrial matrix of liver cells beyond the capacity of the citric acid cycle to process it. The proximate cause is the depletion of oxaloacetate, the TCA cycle entry point for acetyl-CoA. Under fasting, starvation, or insulin-deficient states, oxaloacetate is diverted to gluconeogenesis, simultaneously depleting pyruvate (another acetyl-CoA precursor). This metabolic bottleneck forces the liver to channel excess acetyl-CoA into ketone body synthesis. The three ketone bodies differ in structure and properties: acetoacetate (pKa 3.6) and D-β-hydroxybutyrate (pKa 4.7) are acidic and are the primary metabolically active forms, while acetone is a non-acidic, volatile byproduct formed by spontaneous or enzymatic decarboxylation of acetoacetate (a β-keto acid with a built-in electron sink) and is excreted in urine and breath. Their small size and water solubility allow them to cross the blood-brain barrier — unlike albumin-bound fatty acids, which cannot — making them critical fuel molecules for the brain during prolonged fasting or carbohydrate deprivation.
The ketogenesis pathway begins with the reverse of the thiolase reaction from β-oxidation: two acetyl-CoA molecules undergo a Claisen condensation, catalyzed by ACAT1/thiolase, to form acetoacetyl-CoA and release CoASH. This C–C bond formation is mechanistically the reverse of the thiolytic cleavage in β-oxidation. HMG-CoA synthase then catalyzes the condensation of acetoacetyl-CoA with a third acetyl-CoA to form 3-hydroxy-3-methylglutaryl-CoA (HMG-CoA), proceeding through a ping-pong kinetic mechanism with a covalent acetyl-Cys111 intermediate. The enzyme first accepts an acetyl group from acetyl-CoA at its active-site cysteine (releasing free CoA), then the second substrate, acetoacetyl-CoA, binds and condenses with the enzyme-bound acetyl group via an enolate intermediate, forming a new C–C bond and producing HMG-CoA. This reaction is the committed step of both ketone body synthesis and cholesterol biosynthesis: HMG-CoA is the branch point at which HMG-CoA lyase directs carbon toward ketone bodies and HMG-CoA reductase directs it toward the mevalonate pathway and cholesterol. Statins inhibit HMG-CoA reductase and thus cholesterol synthesis without affecting the lyase-mediated ketogenic route. HMG-CoA lyase cleaves HMG-CoA through an enolate intermediate with the assistance of a zinc-activated water molecule, liberating acetoacetate and acetyl-CoA. The active site residues Arg41, Asp42, His233/235, and Cys266 coordinate the substrate, facilitate enolization, and stabilize the transition state. The mitochondrial enzyme BDH1 then reduces most acetoacetate to D-β-hydroxybutyrate using NADH, increasing the ketone body's water solubility and facilitating blood transport.
In ketolysis, peripheral tissues — including brain, heart, skeletal muscle, and kidney — take up D-β-hydroxybutyrate and acetoacetate via monocarboxylate transporters (MCT1/2). D-β-hydroxybutyrate is first oxidized back to acetoacetate by BDH1 using NAD⁺. Acetoacetate is then activated to acetoacetyl-CoA by succinyl-CoA:3-oxoacid-CoA transferase (SCOT), which transfers the CoA group from succinyl-CoA and bypasses the need for ATP. The liver does not express SCOT and therefore cannot oxidize the ketone bodies it produces—an elegant arrangement that ensures hepatic ketone body output is devoted exclusively to peripheral fueling. Thiolase then cleaves acetoacetyl-CoA into two acetyl-CoA molecules, which enter the TCA cycle to produce ATP. Acetone is a metabolic dead end and is eliminated in urine and expired air, accounting for the characteristic sweet breath odor of ketotic patients.
Insulin tightly regulates ketogenesis as the primary inhibitory hormone. Low insulin — as occurs in fasting, type 1 diabetes, or ketogenic diets — simultaneously increases lipolysis in adipocytes (by relieving inhibition of hormone-sensitive lipase), increases mitochondrial fatty acid import (by reducing malonyl-CoA levels through inactivation of acetyl-CoA carboxylase, which relieves CPT-1 inhibition), and increases HMG-CoA synthase activity. Glucagon, cortisol, thyroid hormones, and catecholamines further stimulate ketogenesis by promoting fatty acid mobilization. Ketoacidosis results when this process is uncontrolled: in diabetic ketoacidosis (DKA), severely impaired glucose utilization drives massive hepatic gluconeogenesis, depleting oxaloacetate, overwhelming the TCA cycle with acetyl-CoA, and producing ketone bodies faster than peripheral tissues can consume them. The resulting low blood pH (acidosis) triggers compensatory deep, rapid breathing (Kussmaul respiration) to eliminate CO₂ and raise pH — potentially causing respiratory alkalosis. Concurrent hyperglycemia draws water from cells by osmosis and impairs renal water reabsorption, causing severe dehydration. DKA is distinct from the mild, controlled ketosis induced by fasting or the ketogenic diet, which can be therapeutically beneficial in conditions such as epilepsy and has been explored as a treatment for PDC deficiency by bypassing glycolysis entirely.
This page titled 17.3: Ketone Bodies was last modified on Mon, 14 Sep 2026 12:19:04 GMT and is shared under a CC BY 4.0 license and was authored, remixed, and/or curated by Henry Jakubowski and Patricia Flatt via source content that was edited to the style and standards of the LibreTexts platform.
The book could not be loaded just now.